Adrenal vein sampling in Cushing’s syndrome with bilateral adrenal lesions (#314)
Case 1:
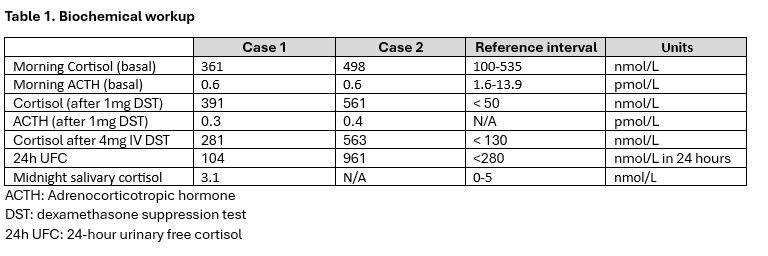
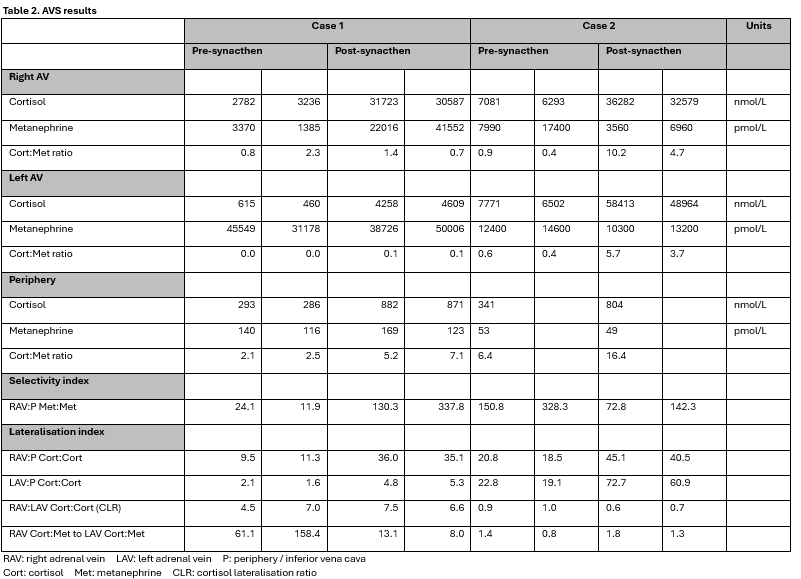
A 48-year-old woman was reviewed for bilateral adrenal lesions (33mm right and 10mm left). In the ensuing year she developed facial swelling and had an L5 fracture. Biochemical investigations (Table 1) showed ACTH-independent autonomous cortisol secretion (ACS), confirming adrenal Cushing’s syndrome (CS). Adrenal vein sampling (AVS) was pursued to aid treatment choice, which demonstrated right-sided dominant cortisol production (Table 2). She underwent right adrenalectomy with histology confirming adrenocortical adenoma.
Case 2:
A 42-year-old woman was investigated for CS in the setting of oligomenorrhoea and osteoporosis. Biochemical workup (Table 1) confirmed ACS. Bilateral adrenal adenomas were identified on CT – 24mm left and 17mm right. She was diagnosed with adrenal CS. AVS suggested bilateral cortisol hypersecretion (Table 2). She underwent a debulking left adrenalectomy after MDM discussion. Histology confirmed adrenocortical adenoma. Hydrocortisone (HC) was started post-operatively and was difficult to wean. She is now 5 years post-op and requiring HC 4mg daily.
Discussion
15-20% of adrenal incidentalomas are bilateral1. Hormonal excess may originate from either one or both lesions. Unilateral ACS is generally managed with unilateral adrenalectomy (UAL). Bilateral ACS management is complex as bilateral adrenalectomy (BAL) results in adrenal insufficiency (AI) while medical therapy's role is not well-established. UAL targeting the larger gland can be considered, however adrenal size does not always correlate with the degree of hypercortisolaemia2,3.
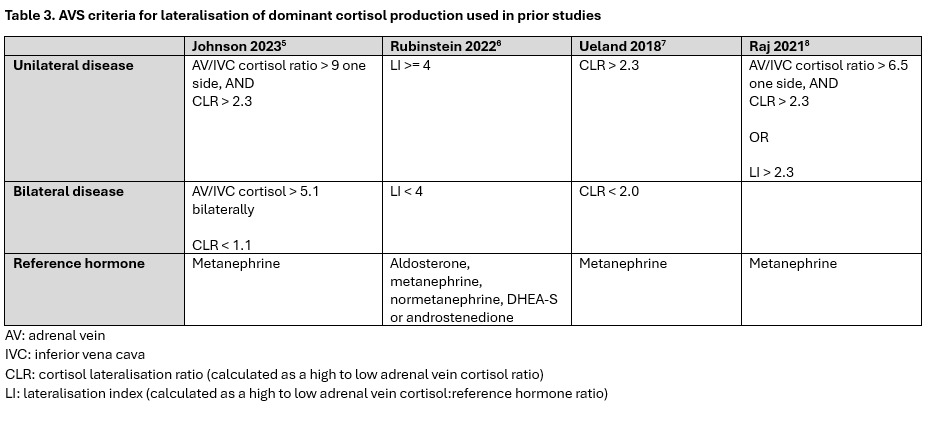
AVS helps localise the surgical target in bilateral ACS, however there is limited data to validate interpretation criteria. In ACS, cortisol is the target hormone and an alternative, such as metanephrine, is used as reference hormone to determine cannulation success4. Several parameters were recommended to assess for lateralisation (Table 3)5-8. In one study, 0/13 patients with predicted unilateral ACS had recurrence post-UAL5. Lastly, UAL targeting the side with higher AV/IVC-cortisol-ratio may still lead to remission in AVS-proven bilateral ACS5-7.
- Fassnacht, Martin et al. “European Society of Endocrinology clinical practice guidelines on the management of adrenal incidentalomas, in collaboration with the European Network for the Study of Adrenal Tumors.” European journal of endocrinology vol. 189,1 (2023): G1-G42. doi:10.1093/ejendo/lvad066
- Debillon, Emmanuelle et al. “Unilateral Adrenalectomy as a First-Line Treatment of Cushing's Syndrome in Patients With Primary Bilateral Macronodular Adrenal Hyperplasia.” The Journal of clinical endocrinology and metabolism vol. 100,12 (2015): 4417-24. doi:10.1210/jc.2015-2662
- Sandooja R, Hamidi O, Zhang CD, et al. Bilateral Adrenal Nodules Presenting With Mild Autonomous Cortisol Secretion. Endocr Pract. 2025;31(8):1071-1083. doi:10.1016/j.eprac.2025.06.019
- Dekkers, Tanja et al. “Plasma metanephrine for assessing the selectivity of adrenal venous sampling.” Hypertension (Dallas, Tex. : 1979) vol. 62,6 (2013): 1152-7. doi:10.1161/HYPERTENSIONAHA.113.01601
- Rubinstein, German et al. “The role of adrenal venous sampling (AVS) in primary bilateral macronodular adrenocortical hyperplasia (PBMAH): a study of 16 patients.” Endocrine vol. 76,2 (2022): 434-445. doi:10.1007/s12020-022-03020-z
- Ueland, Grethe Å et al. “Adrenal Venous Sampling for Assessment of Autonomous Cortisol Secretion.” The Journal of clinical endocrinology and metabolism vol. 103,12 (2018): 4553-4560. doi:10.1210/jc.2018-01198
- Raj, Rishi et al. “Adrenal Vein Cortisol to Metanephrine Ratio for Localizing ACTH-Independent Cortisol-Producing Adenoma: A Case Report.” Journal of the Endocrine Society vol. 5,4 bvab009. 25 Jan. 2021, doi:10.1210/jendso/bvab009