Balancing efficacy and rebound risk: extending denosumab dosing intervals in low-risk patients (#388)
Background: Denosumab is the most used osteoporosis therapy in Australia. However, uncertainty remains regarding the long‑term consequences of sustained bone turnover suppression beyond 10 years and the optimal duration of therapy, particularly in younger individuals and those at low fracture risk. It is unclear whether strategies that allow partial recovery of bone turnover, such as extended dosing intervals (EDI), may reduce skeletal adverse effects whilst maintaining bone mineral density (BMD). We assessed the safety of EDI and its ability to preserve BMD following long‑term treatment.
Methods: We report 19 women receiving denosumab in whom the dosing interval was extended from six to 7–9 monthly. All patients had achieved osteopenic or stable osteoporotic BMD prior to EDI, and were considered to have low fracture risk. Risks were discussed and informed consent provided.
Results: The median age of the cohort was 68 years (IQR 62-79), with a median denosumab treatment duration of 9.2 years (IQR 6.8-10.8). The median lumbar spine (LS) T-score was -1.3 (IQR -0.9 to -1.6), total hip (TH) T-score -2.0 (IQR -1.4 to -2.4). Nine patients had never sustained a fragility fracture. At a median follow‑up of 1.8 years (IQR 1.0-4.2 years) after interval extension, LS and TH BMD remained stable with a median percentage change in LS 0.8% (IQR -1.9 to 1.9) and TH -0.3% (IQR -1.0 to 1.9). Two patients who inadvertently extended the dosing interval to 10 months, lost BMD in both their LS and TH. No clinical vertebral or non‑vertebral fractures were observed.
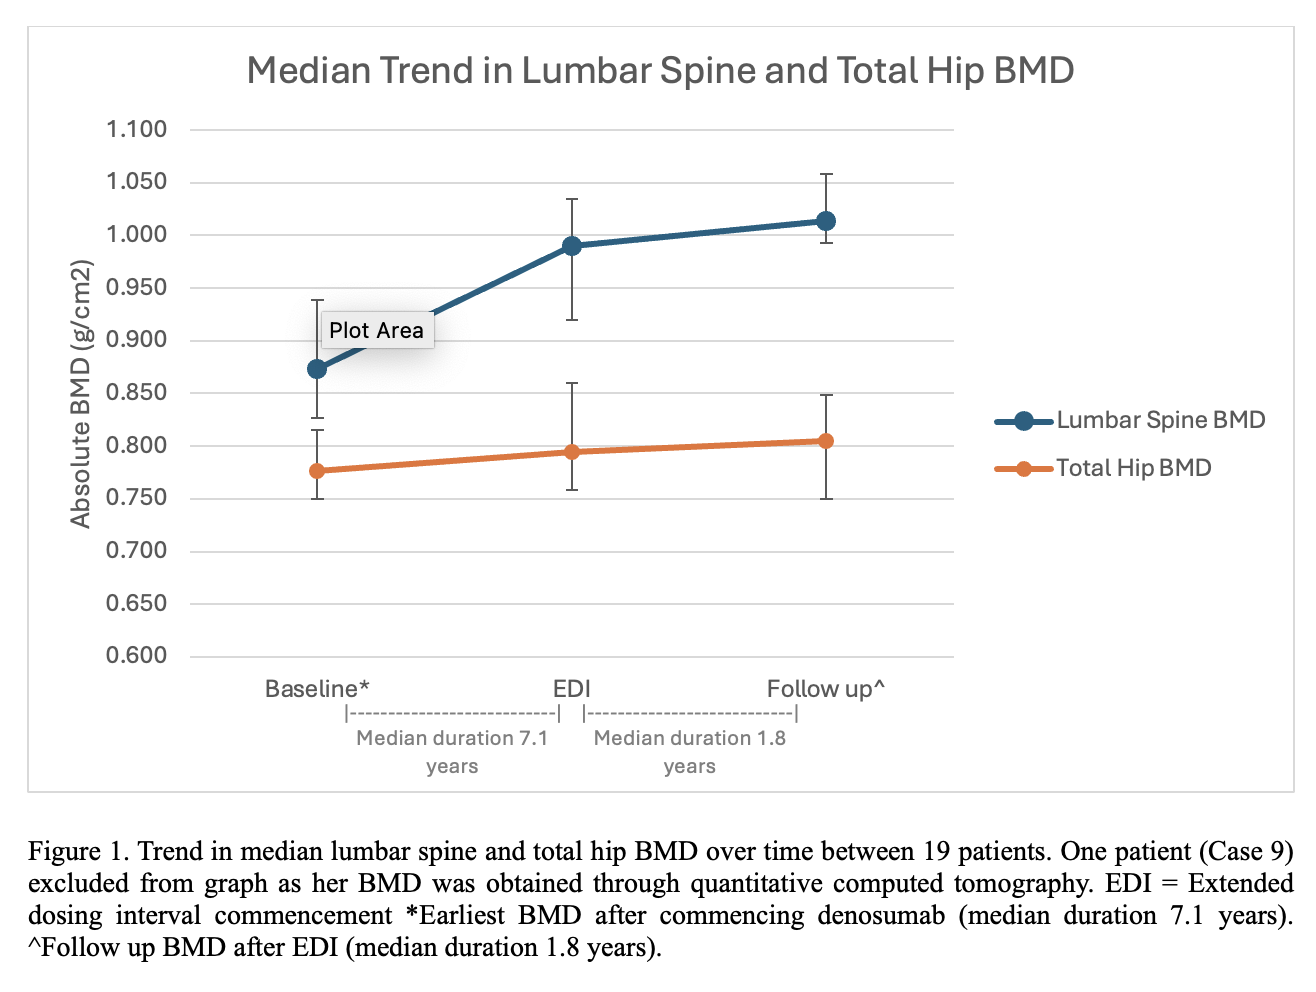
Conclusion: These findings suggest that modest denosumab interval extension may maintain BMD in a population with low fracture risk and require confirmation in larger prospective controlled studies. Given the risks of rebound, these strategies must be cautiously applied, limited to carefully selected patients, and undertaken with close specialist supervision.
