The Downfall of Cortisol: Osilodrostat in Ectopic Cushing’s (#460)
Case Presentation
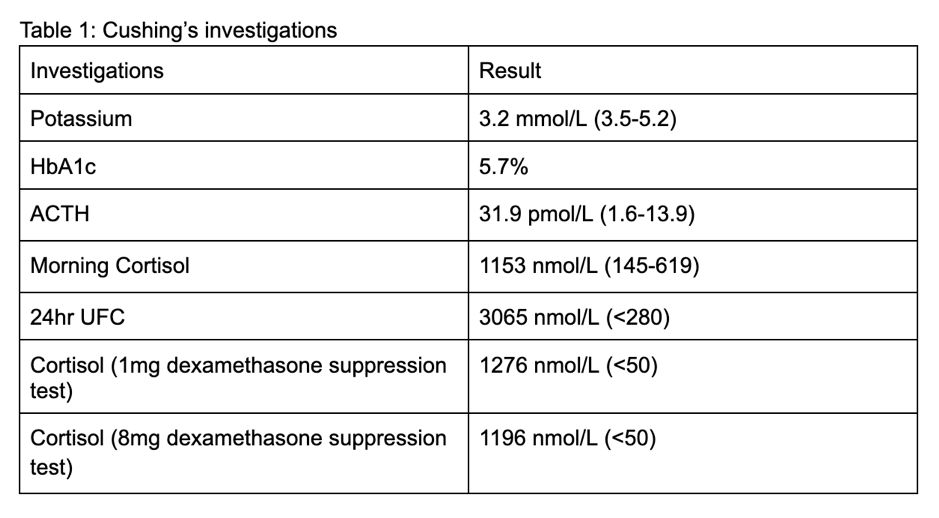
A 78-year-old man presented with a 3-month history of rapidly progressive hypercortisolism, including proximal myopathy, fatigue, 5kg weight gain, easy bruising, oedema, facial plethora, and worsening hypertension. Examination demonstrated moon facies, central adiposity, peripheral wasting, thin skin, and hypertension. Biochemical testing confirmed severe ACTH-dependent Cushing’s syndrome with markedly elevated urinary free cortisol, failure to suppress on low- and high-dose dexamethasone testing, elevated ACTH (31.9 pmol/L), and spontaneous hypokalaemia (table 1).
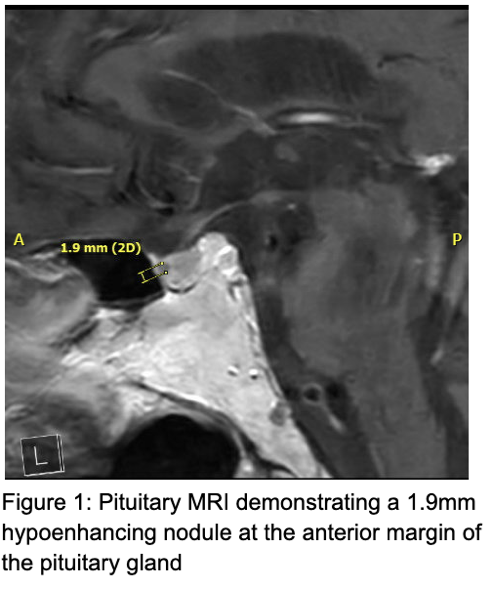
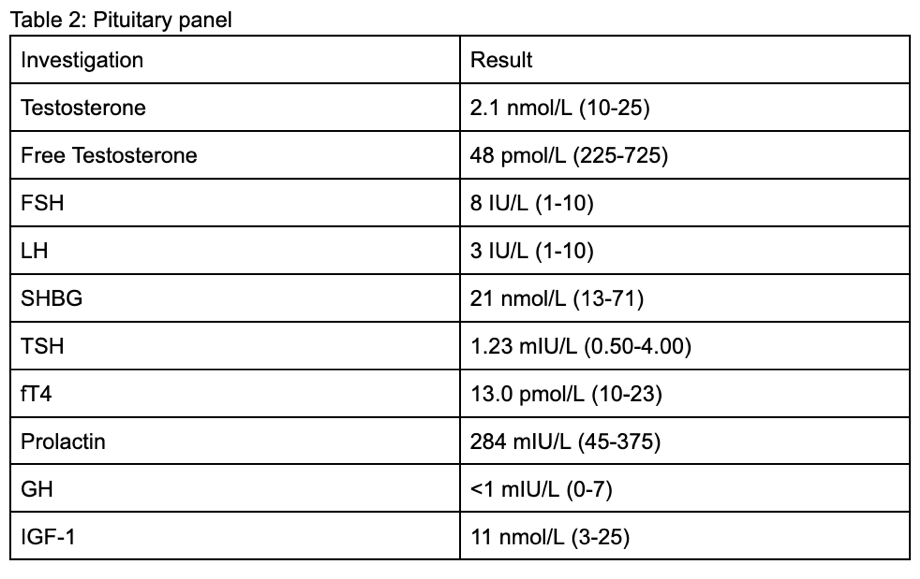
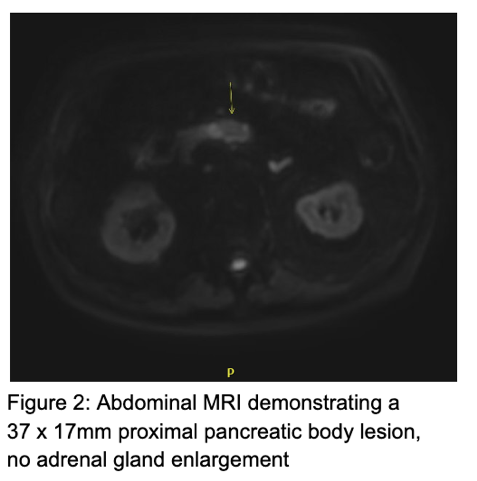
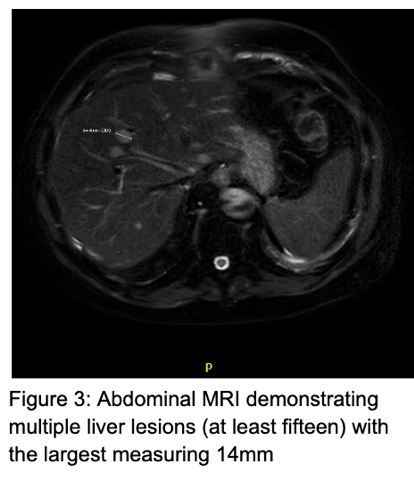
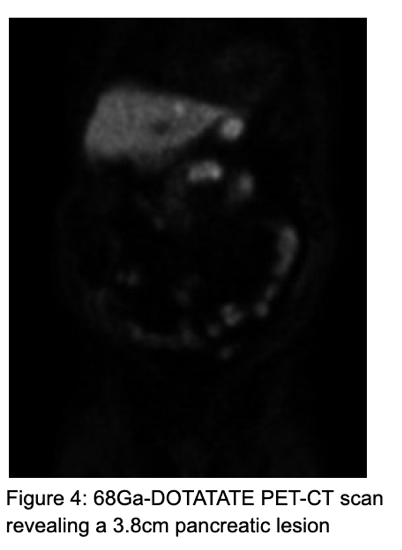
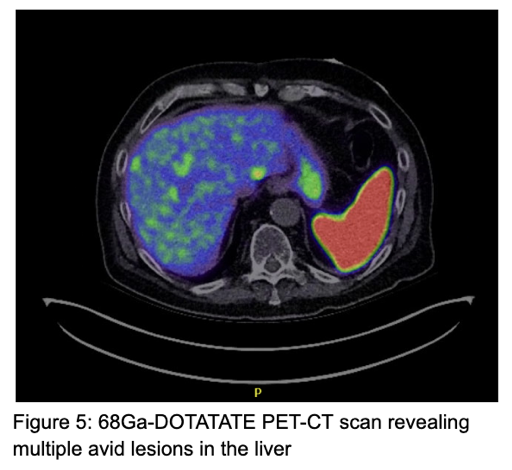
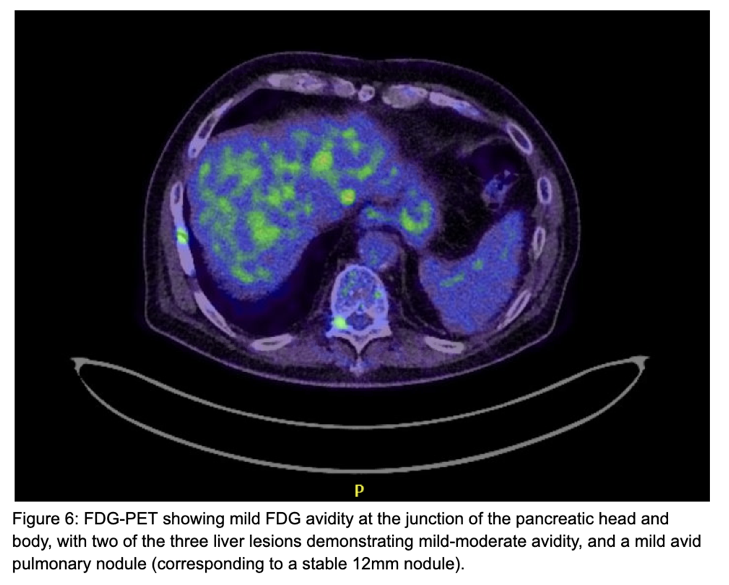
Pituitary MRI identified an incidental non-functional microadenoma (figure 1, table 2), and abdominal MRI demonstrated a pancreatic hyperenhancing lesion with multiple hepatic metastases (figure 2, 3). Given the rapid clinical progression and imaging suggestive of metastatic pancreatic neuroendocrine tumour (PNET), inferior petrosal sinus sampling was deferred until pancreatic biopsy. Endoscopic ultrasound-guided biopsy confirmed an ACTH-producing metastatic Grade 2 PNET, with DOTATATE- and FDG-PET imaging demonstrating liver metastases (figure 4, 5, 6).
Osilodrostat was commenced at 5mg twice daily and rapidly increased to 10mg twice daily. A block-and-replace strategy was implemented, initially with dexamethasone followed by hydrocortisone after adequate cortisol suppression (figure 7, 8). Lanreotide was commenced as tumour-directed therapy.
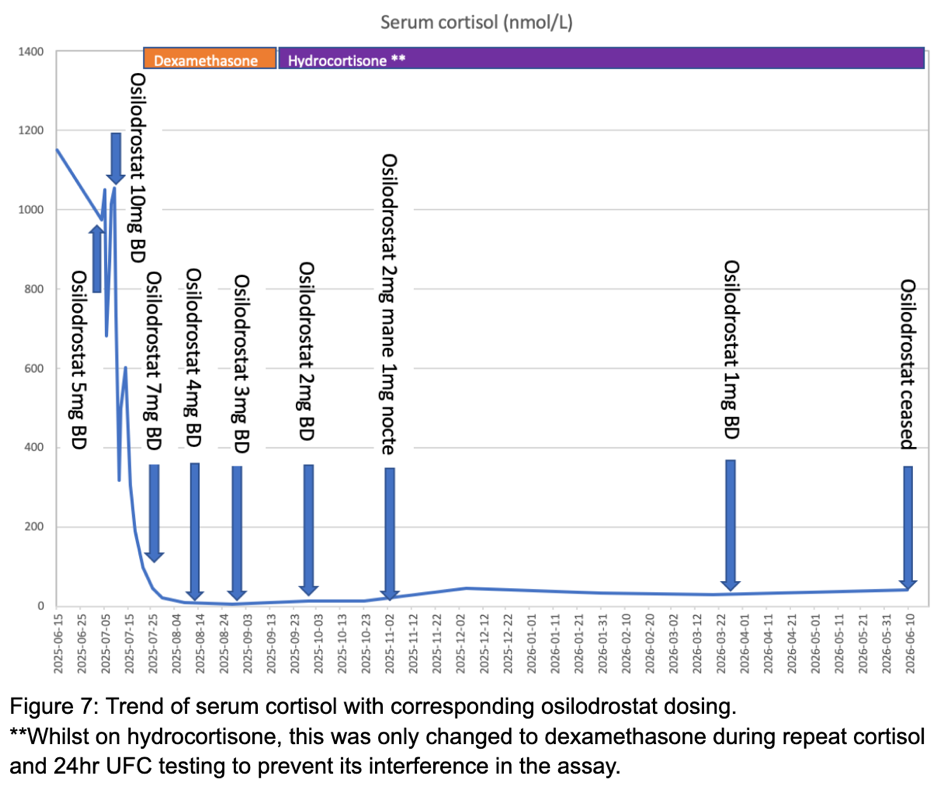
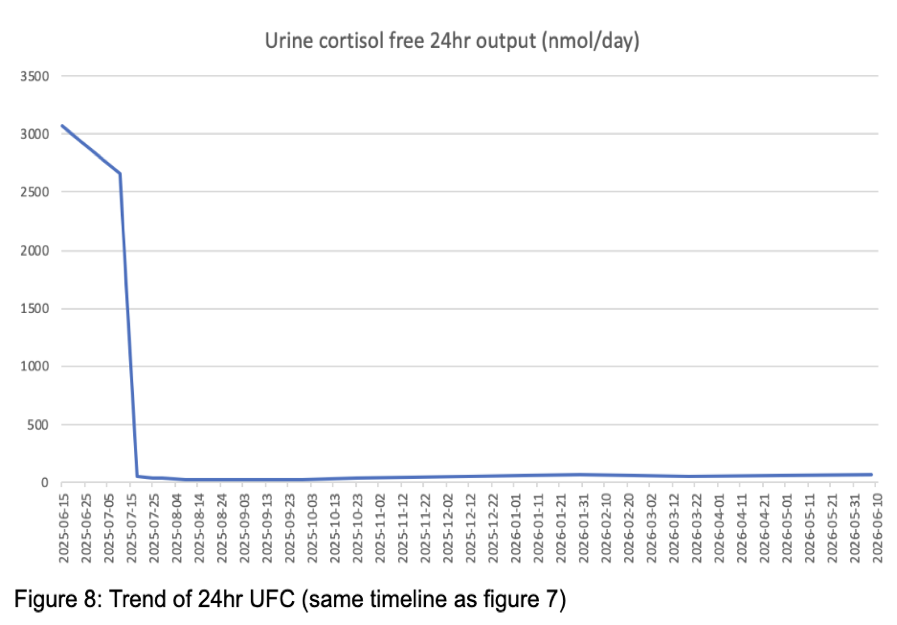
Treatment resulted in rapid biochemical and clinical improvement, including normalisation of serum potassium, blood pressure, hypogonadotropic hypogonadism, and marked symptom resolution. Serial monitoring demonstrated sustained remission, allowing cessation of osilodrostat while continuing physiological hydrocortisone replacement.
Discussion
Osilodrostat is a potent 11β-hydroxylase inhibitor with increasing evidence supporting its use in ectopic Cushing’s syndrome (1, 2). Although randomised data are largely limited to Cushing’s disease, observational studies demonstrate rapid and substantial cortisol reduction in ectopic disease (3, 4). There are two main strategies in utilising osilodrostat: titration and block-and-replace (3, 5) with this case highlighting the effectiveness of a block-and-replace strategy in severe hypercortisolism, while emphasising the importance of close monitoring for adrenal insufficiency throughout treatment and following drug withdrawal.
- Fleseriu, M., Auchus, R.J., Bancos, I. and Biller, B.M., 2025. Osilodrostat treatment for adrenal and ectopic Cushing syndrome: integration of clinical studies with case presentations. Journal of the Endocrine Society, 9(4), p.bvaf027.
- Tabarin, A., Bertherat, J., Decoudier, B., Lasolle, H., Lefebvre, H., Drui, D., Vaillant, C., Morera, J., Castinetti, F., Cristante, J. and Chevalier, N., 2024. SAT-671 Safety And Effectiveness Of Osilodrostat In Patients With Non-Pituitary Cushing’s Syndrome:
- Dormoy, A., Haissaguerre, M., Vitellius, G., Do Cao, C., Geslot, A., Drui, D., Lasolle, H., Vieira-Pinto, O., Salenave, S., François, M. and Puerto, M., 2023. Efficacy and safety of osilodrostat in paraneoplastic Cushing syndrome: a real-world multicenter study in France. The Journal of Clinical Endocrinology & Metabolism, 108(6), pp.1475-1487.
- Tabarin, A., Bertherat, J., Decoudier, B., Lasolle, H., Lefebvre, H., Drui, D., Vaillant, C., Morera, J., Castinetti, F., Cristante, J. and Chevalier, N., 2026. Real-world osilodrostat effectiveness and safety in nonpituitary Cushing syndrome. The Journal of Clinical Endocrinology & Metabolism, 111(5), pp.1287-1298.
- Araujo-Castro, M., Lamas, C., Nowak, E., Newell-Price, J., Reincke, M. and Castinetti, F., 2026. Update and practical recommendations for the use of medical treatment of Cushing´ s syndrome. Endocrine Reviews, p.bnaf042.
