Relative aldosterone insufficiency after glucocorticoid replacement in 17α-hydroxylase/17,20-lyase deficiency (#453)
Aims
17α-hydroxylase/17,20-lyase deficiency (17OHD), a rare form of congenital adrenal hyperplasia (CAH), is caused by biallelic CYP17A1 mutations [1]. Marked clinical heterogeneity often delays diagnosis, compromising prognosis [1]. This study reports a 40-year-old woman presenting with renal impairment who was diagnosed with 17OHD, highlighting clinical features and treatment complexities to raise awareness of standardized management.
Methods
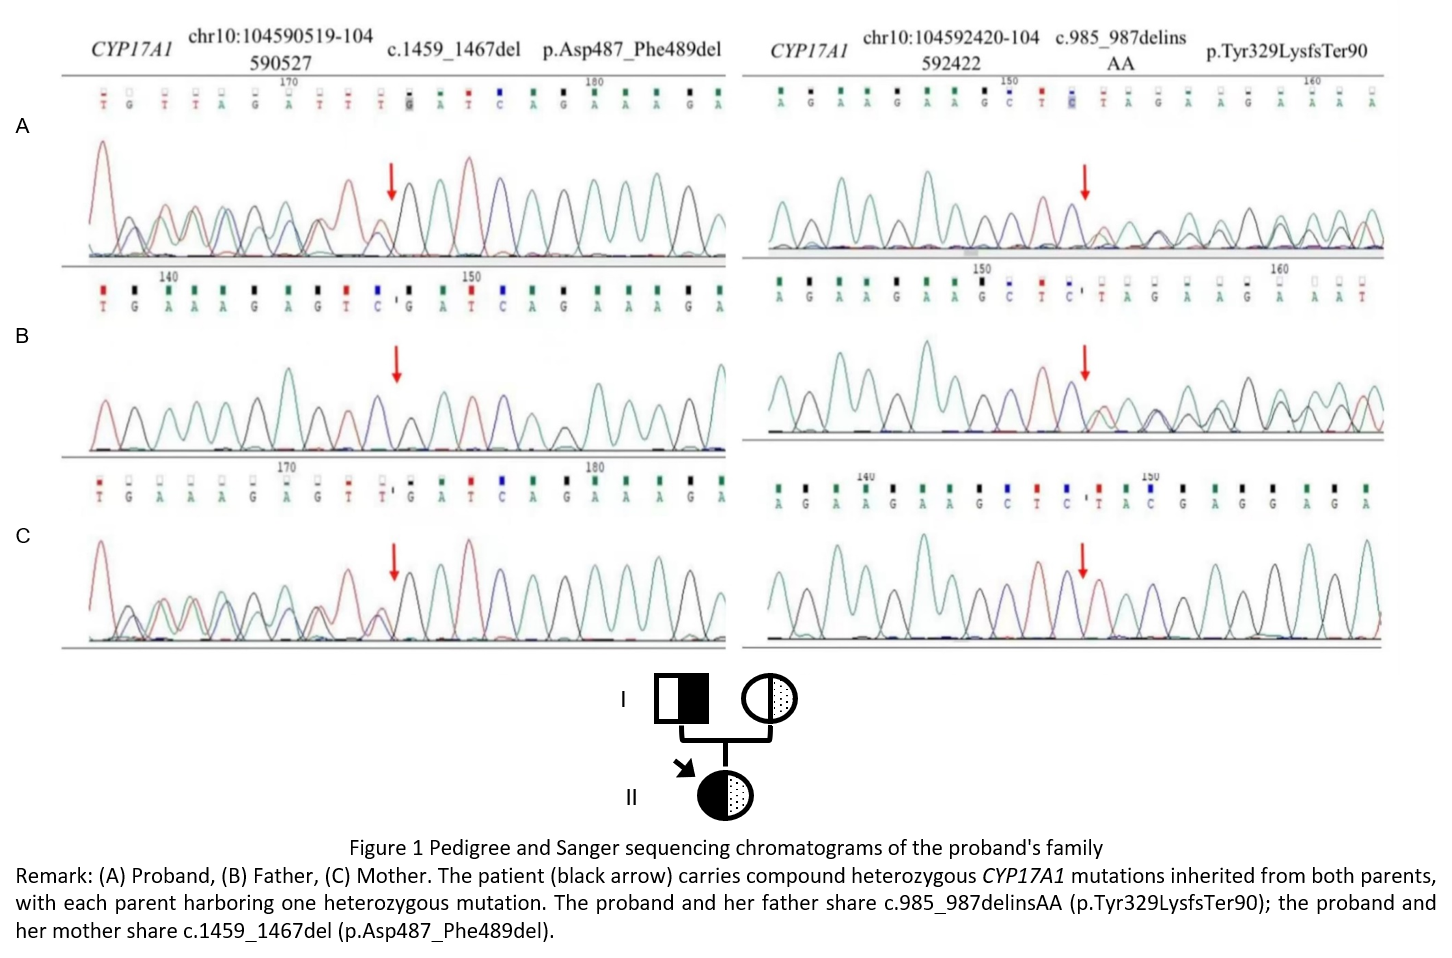
Comprehensive endocrine evaluation, adrenal imaging, and karyotyping were performed. Whole-exome sequencing identified compound heterozygous CYP17A1 mutations, confirmed by Sanger sequencing in both parents.
Results
A 40-year-old phenotypic female with untreated hypertension and primary amenorrhea presented to nephrology with foamy urine, renal impairment, and incidentally detected hypokalemia. Refractory hypertension (five antihypertensives including spironolactone) and persistent hypokalemia prompted endocrine referral. Physical examination revealed sexual infantilism. Laboratory findings showed hypergonadotropic hypogonadism, low cortisol (8 AM: 18.0 nmol/L; elevated ACTH (8 AM: 94.1 pg/mL), suppressed renin and aldosterone, and high-turnover bone loss. Abdominal CT showed bilateral adrenal hyperplasia with absent uterus. Karyotype analysis revealed 46,XX. Whole-exome sequencing (Figure 1) identified compound heterozygous CYP17A1 mutations, confirmed by Sanger sequencing in both parents. She was diagnosed with 17OHD and started on dexamethasone 0.375 mg nightly. Blood pressure and potassium improved with declining ACTH, but hyperkalemia occurred after 1 months. This reflected relative aldosterone insufficiency: dexamethasone suppressed ACTH and 11-deoxycorticosterone (DOC) synthesis, while chronic renin–angiotensin–aldosterone system suppression from prior DOC excess had downregulated zona glomerulosa CYP11B2, preventing timely aldosterone compensation [2,3]. Reduced renal function further impaired potassium excretion [4]. Fludrocortisone replacement normalized potassium, confirming relative aldosterone deficiency.
Conclusion
This case highlights that hereditary adrenal disorders should be suspected in patients with sexual infantilism, hypertension, and hypokalemia regardless of age. 17OHD replacement requires dynamic monitoring of electrolytes and hormones to balance glucocorticoid and mineralocorticoid doses. Early diagnosis, standardized treatment, and long-term organ protection are crucial for prognosis.
- Willemsen AL, Torpy DJ, De Sousa SMC, Falhammar H, Rushworth RL. 17α-Hydroxylase/17,20-lyase Deficiency (17-OHD): A Meta-analysis of Reported Cases. J Clin Endocrinol Metab. 2025 Mar 17;110(4):e1261-e1271. doi: 10.1210/clinem/dgae773. PMID: 39500362; PMCID: PMC11913080.
- Raff H, Gehrand A, Bruder ED, Hoffman MJ, Engeland WC, Moreno C. Renin knockout rat: control of adrenal aldosterone and corticosterone synthesis in vitro and adrenal gene expression. Am J Physiol Regul Integr Comp Physiol. 2015 Jan 1;308(1):R73-7. doi: 10.1152/ajpregu.00440.2014. Epub 2014 Nov 12. PMID: 25394830; PMCID: PMC4281677.
- Volpe M, Rubattu S, Gigante B, Ganten D, Porcellini A, Russo R, Romano M, Enea I, Lee MA, Trimarco B. Regulation of aldosterone biosynthesis by adrenal renin is mediated through AT1 receptors in renin transgenic rats. Circ Res. 1995 Jul;77(1):73-9. doi: 10.1161/01.res.77.1.73. PMID: 7788884.
- Ikeya A, Yamashita M, Kakizawa K, Kawauchi Y, Matsushita A, Fujisawa Y, Ogata T, Sasaki S. 17α-hydroxylase/17,20-lyase Deficiency Diagnosed at 45 Years of Age with Hyperaldosteronism. Intern Med. 2024 Nov 15;63(22):3071-3076. doi: 10.2169/internalmedicine.3084-23. Epub 2024 Apr 9. PMID: 38599871; PMCID: PMC11637798.