Therapeutic benefit of semaglutide in non-insulinoma pancreatogenous hypoglycaemia syndrome (#454)
Background: Non-insulinoma pancreatogenous hypoglycaemia syndrome (NIPHS) is an uncommon cause of hypoglycaemia, characterised by diffuse pancreatic beta-cell hyperplasia. Traditional pharmacological therapies are limited by variable efficacy and adverse effects. We describe success with semaglutide in a patient with NIPHS.
Case presentation: A 17-year-old female presents with a four-month history of recurrent post-prandial hypoglycaemia. Her medical history included class II obesity (weight 108 kg; BMI 37.8 kg/m2), endometriosis and suspected polyendocrine metabolic ovarian syndrome. There was no family history of hypoglycaemia. Baseline thyroid function, cortisol, IGF-1 and growth hormone, was unremarkable. A mixed meal test did not reproduce hypoglycaemia. A supervised 72-hour fast was terminated at 68 hours demonstrating endogenous hyperinsulaemic hypoglycaemia as represented in Table 1.
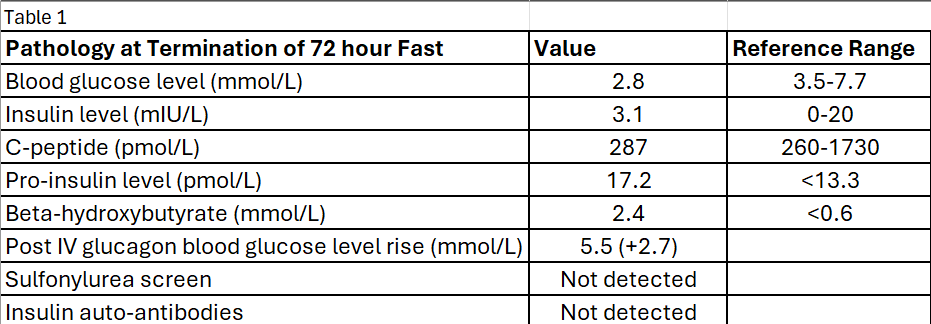
Pancreatic MRI did not identify a focal lesion. DOTATATE-PET demonstrated diffuse pancreatic uptake. Exendin-4 PET/CT also demonstrated diffuse pancreatic uptake, supporting a diagnosis of NIPHS. Selective arterial calcium stimulation testing was not performed.
Management: Acarbose was not tolerated due to gastrointestinal adverse effects. The patient declined a trial of diazoxide and octreotide. Due to concomitant obesity, semaglutide was commenced and uptitrated from 0.25 mg to 2.4 mg weekly. Treatment resulted in reduced frequency of hypoglycaemia and improved continuous glucose monitoring parameters as shown in Table 2. Weight also decreased by 10 kg resulting in BMI 34.2 kg/m2.
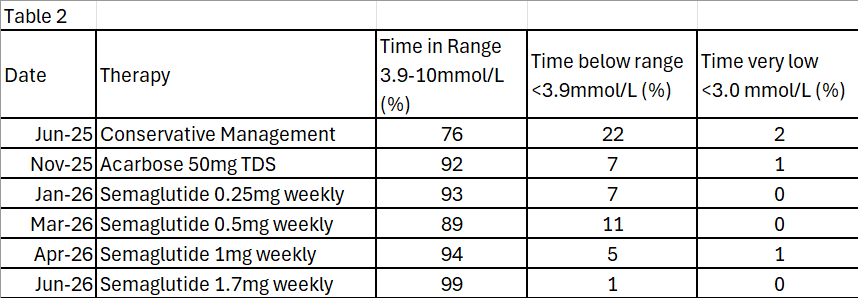
Conclusion: This case highlights a paradoxical improvement in NIPHS-associated hypoglycaemia with semaglutide. This may be due to its glucose-dependent incretin properties which prevent an exaggerated insulin response and glucagon suppression in relative hypoglycaemia (1). In the literature, there is one case report of liraglutide which terminated hypoglycaemia in a 39-year-old female with NIPHS (2). There is mixed efficacy in patients with post-bariatric hypoglycaemia (3,4). Semaglutide should be considered in selected patients with NIPHS and obesity. However, further studies are required to clarify efficacy and durability of response.
- Eisa, N. and O. Barood (2026). "Effects of Semaglutide on Dumping Syndrome and Reactive Hypoglycemia After Bariatric Surgery: A Systematic Review and Meta-Analysis." Obesity Reviews n/a(n/a): e70161.
- Witczak FIJ, editor Noninsulinoma pancreatogenous hypoglycemia syndrome (NIPHS)- a therapeutic challenge. Society for Endocrinology National Clinical Cases 2022 2022.
- Abrahamsson N, Engström BE, Sundbom M, Karlsson FA. GLP1 analogs as treatment of postprandial hypoglycemia following gastric bypass surgery: a potential new indication? European Journal of Endocrinology. 2013;169(6):885-9.
- Øhrstrøm CC, Worm D, Højager A, Andersen D, Holst JJ, Kielgast UL, et al. Postprandial hypoglycaemia after Roux-en-Y gastric bypass and the effects of acarbose, sitagliptin, verapamil, liraglutide and pasireotide. Diabetes, Obesity and Metabolism. 2019;21(9):2142-51.