Hemichorea Unmasking Uncontrolled Diabetes Mellitus: A Case of Diabetic Striatopathy. (#407)
Background :
Diabetic Striatopathy (DS) also termed as hyperglycaemic hemichorea- hemiballismus (HCHB) syndrome, is a rare neurometabolic complication of poorly controlled diabetes1. It is characterised by unilateral chorea or ballismus with contralateral basal ganglia abnormalities on neuroimaging in the setting of marked hyperglycaemia1. We report a case of diabetic striatopathy presenting as hemichorea with poorly controlled diabetes.
Case Study:
A 65-year-old woman presented with severe left-sided hemichorea involving the upper and lower limbs, resulting in recurrent skin abrasions. She reported several weeks of osmotic symptoms, unintentional weight loss (>5 kg) and had discontinued her diabetic medications for three months. Her medical history included type 2 diabetes, transient ischemic attacks , sarcoidosis, hypertension and dyslipidaemia. Neurological examination demonstrated mild expressive aphasia with prominent left- sided hemichorea. CT brain (Stroke protocol) demonstrated asymmetric hyperdensity within the right basal ganglia without evidence of acute infarct. MRI brain confirmed T1 hyperintensity of the right putamen consistent with DS.
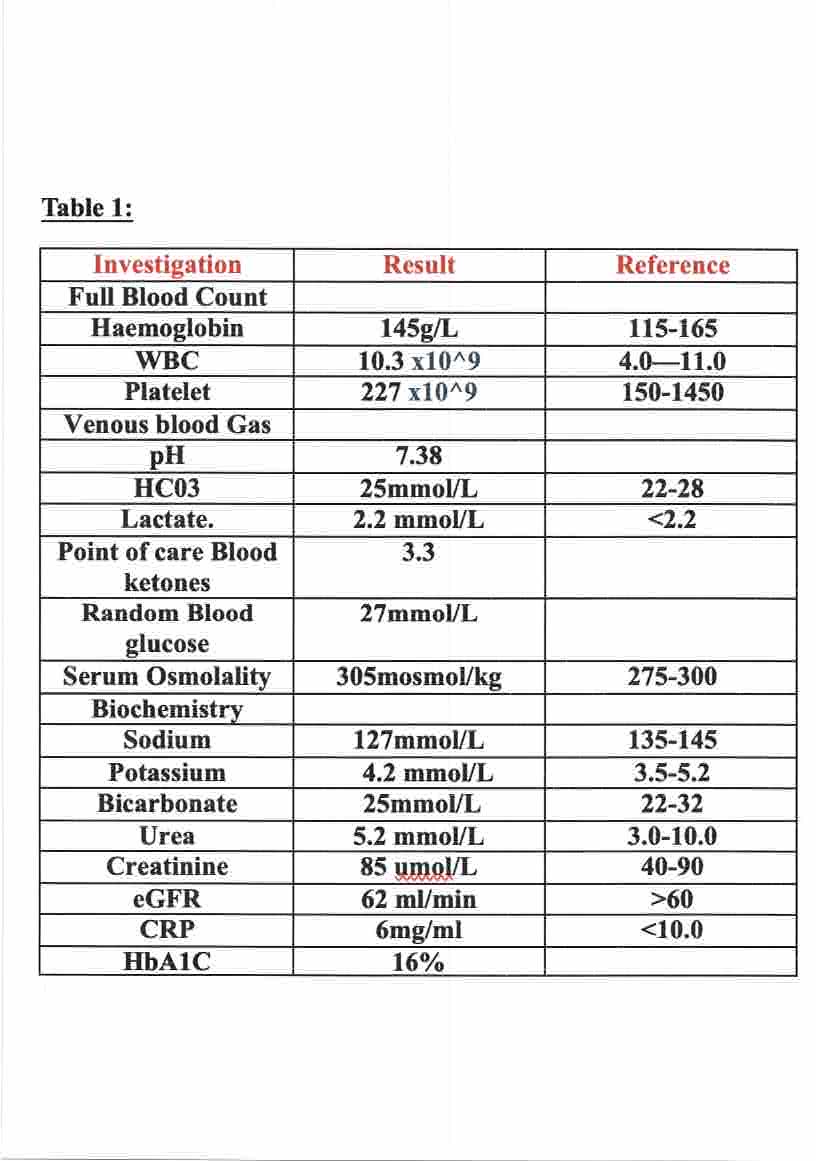
She had severe hyperglycaemia with ketosis (Table 1) and was commenced on basal-bolus insulin regimen. Haloperidol (0.5mg twice daily) initially improved symptoms but symptoms reoccurred after its cessation. Tetrabenazine (25mg nocte) provided modest benefit. Adjunctive clonazepam (0.5mg twice daily) caused daytime somnolence and was discontinued following neurology review. Hemichorea improved markedly following optimisation of glycaemic control, allowing mobilisation with a four wheeled walker despite mild residual deficits.
Conclusion:
This case highlights the importance of recognising DS as a reversible complication of poorly controlled diabetes. Timely identification of glycaemic control can reverse metabolic and neurological complications, although residual deficits may persist.2,3
Discussion:
First described in 1960, DS is a rare condition with fewer than 200 cases reported.2,4 Proposed mechanisms include hyperglycaemia-induced hyperviscosity, transient striatal ischemia and impaired basal ganglia neurotransmitter metabolism3. Early recognition of this clinicoradiological syndrome enables prompt treatment and may avoid unnecessary investigations.4
- 1. ML Chenler et al. A case of diabetic striatopathy due to uncontrolled type 2 diabetes. EDM Case Reports (2024) 2024 e230082 2. A Arecco et al. Diabetic striatopathy: an updated overview of current knowledge and future perspectives. J Endocrinol Invest, 2023 Aug 14;47(1):1-15 3. Subhankar Chatterjee et al. Irreversible Diabetic Striatopathy in Reversible Diabetes. JCEM Case Rep 2026 Jan 6;4(1): luaf292 4. Chua CB et al. “Diabetic Striatopathy” clinical presentations, controversy, pathogenesis, treatments, and outcomes. Scientific Reports 2020 10 1594